
Dr Dirk J Booysen
Dip Optom FOA(SA), MC Optom (UK), TMOD (US), CAS (NECO), D Optom (UK), FSLS
Population data, SA
- 54,490,000 residents in ZAR (2015), expected to rise to 65,540,00 by 2050
- 8% of population > 60 years
- 40 million receive care in the public sector
- 79% percent of the population, since the end of apartheid, self-identifies as Black
- Median age at Death: 57 years
- Source: www.unpopulation.org
Number of ophthalmologists in South Africa-2012
- 324 Ophthalmologists in South Africa, only 70 of these in public sector
- Only 82% doing surgery
- This averages 6 ophthalmologists per million of population overall
- Only 70 in public sector – serving 40 million people or 1:500,000
- IOC also states that the number of ophthalmologists unlikely in SA unlikely to change
Number of Optometrists in South Africa
- 3500 Optometrists
- Ratio 1:17,000 considering total population
- Majority in private sector dealing with less than 10 million people, ratio 1:3000
- Very few in public sector (< 100), ratio 1:4 Million
- Due in part to the lack of public sector posts
- Very few involved in primary eye care
- Due to restriction on scope of the profession
- Inadequate training
What is the ideal ratio for Africa?
According to the WHO:
- Ophthalmology 1:250,000
- Optometry 1:10,000
Currently Ophthalmology averages around 1:1 million and Optometry 1:100,000
“Every country with a population of > 20 million needs at least 1 institution offering an Optometry programme”*
What about the quality of education and scope of practice?
*Oduntan et al. Optometry and Vision Science. March 2014, Vol. 91(3)
Global causes of blindness
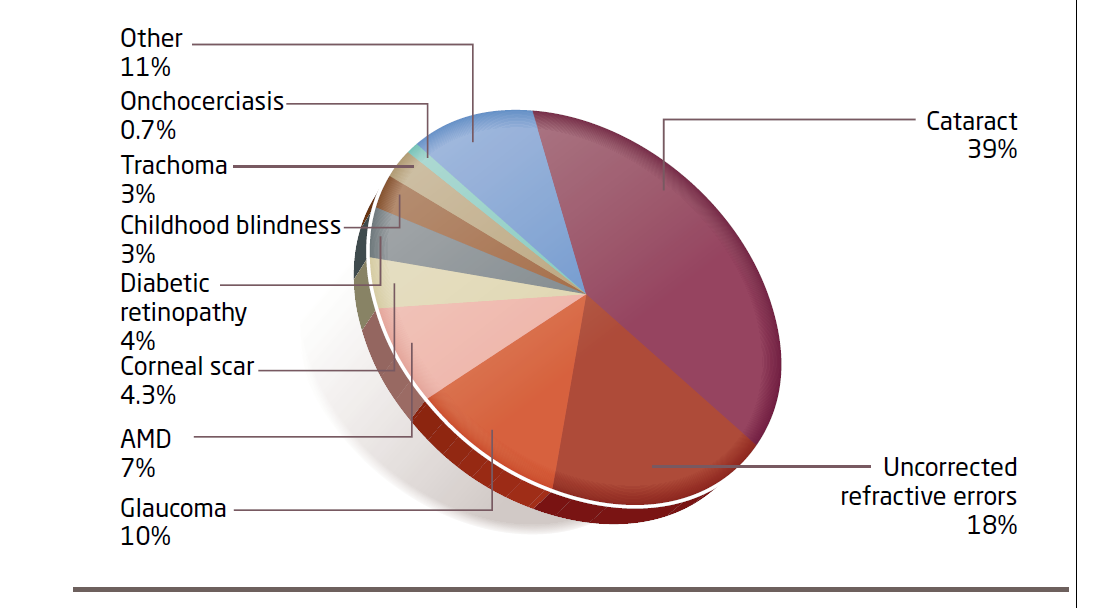
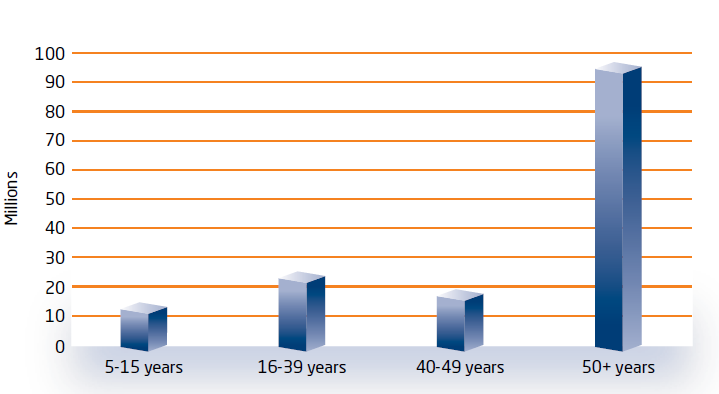
153 million people with visual impairment due to refractive error – acuity < 6/18
Refractive error is the main cause of visual impairment in the 5 – 15yr old group globally
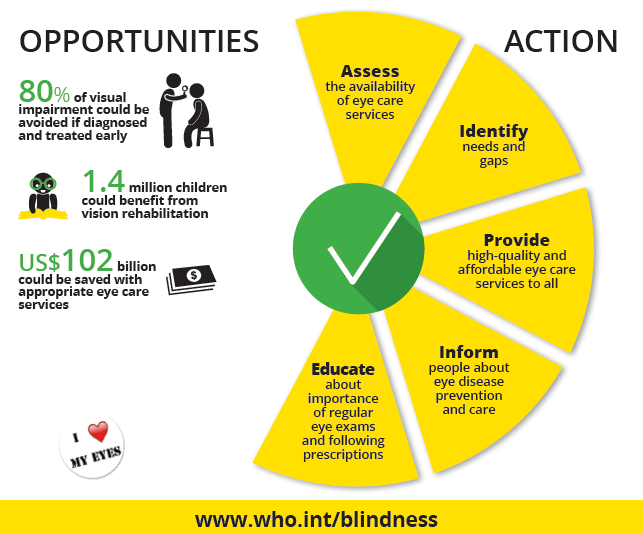
What can be done globally?
Causes of blindness in Africa
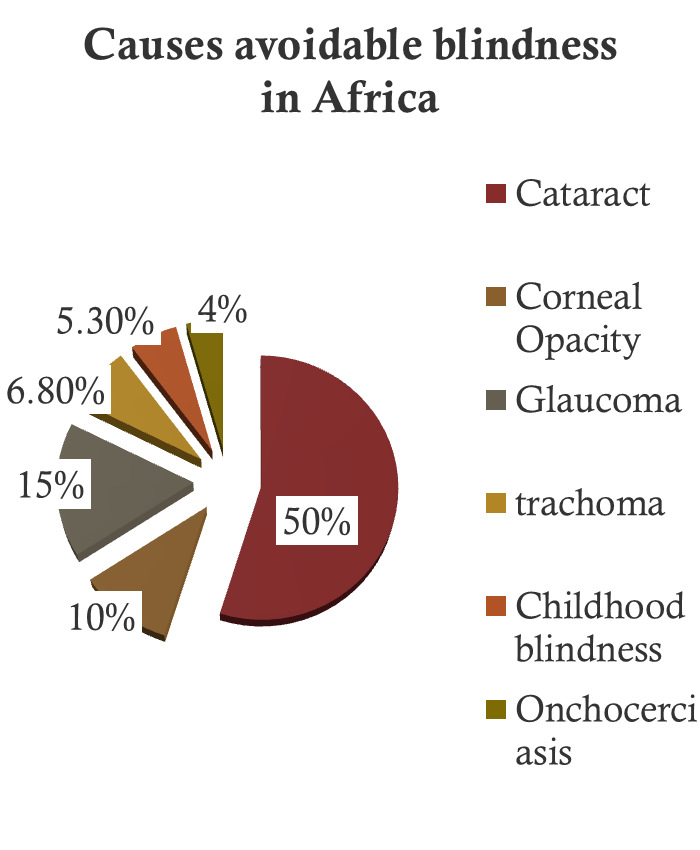
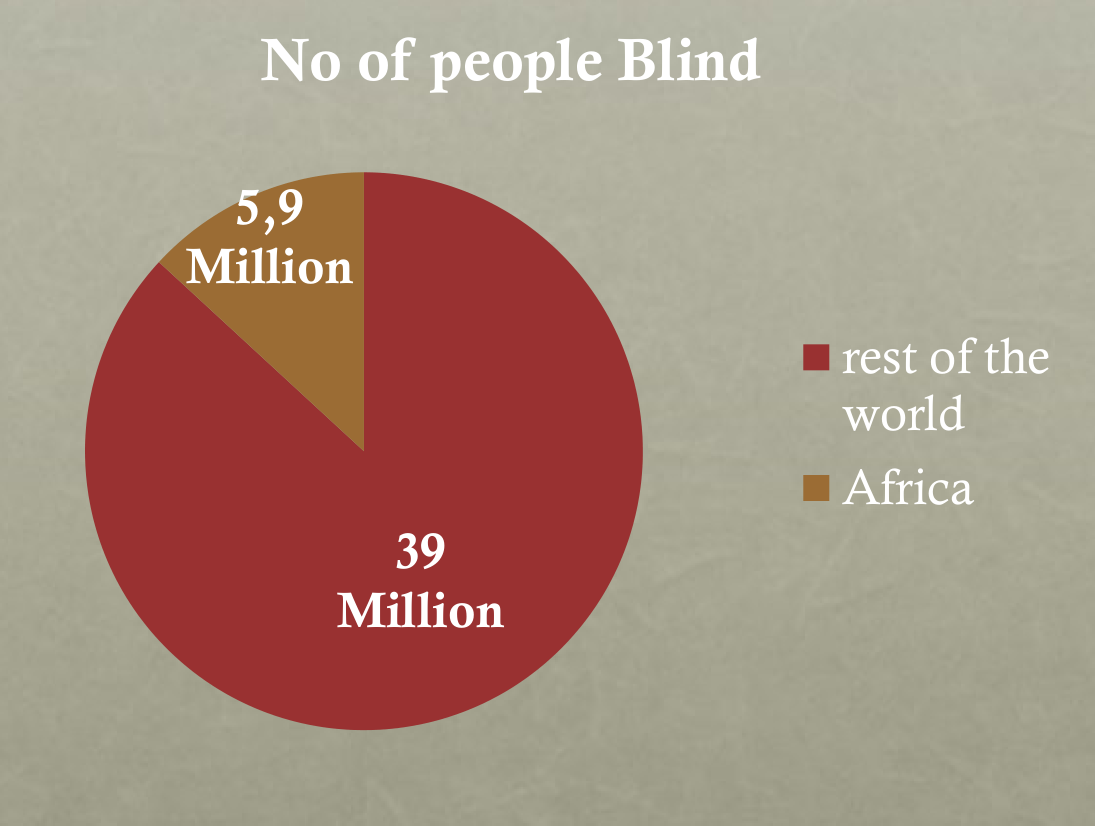
What about blindness caused by refractive error?
18% globally, probably much higher in Africa
Causes of preventable blindness
- Cataract – prevalence from 5% in developed countries to 50% in poorer regions. Major non- modifiable risk factor is ageing
- Refractive errors and low vision – > 18% globally
- Trachoma – Endemic in 55 countries. 10.6 million people in need of entropion surgery to prevent corneal scarring and 5.9 million irreversibly visually impaired from trachoma
- Onchocerciasis – 37 million people affected in West, Central and East Africa. 300, 000 blind from onchocerciasis
- Glaucoma – world wide 4.5 million blind from POAG and 3.9 million blind from PCAG. More than 61 million will have glaucoma (2010)
- Diabetic retinopathy – responsible for 4.8% of the 39 million blind due to eye disease in the world. World wide 415 million people have diabetes, this figure will double by 2040.
Health care costs of diabetes range from 2.5% to 15% of annual health care budgets
Prevalence of glaucoma in Africa
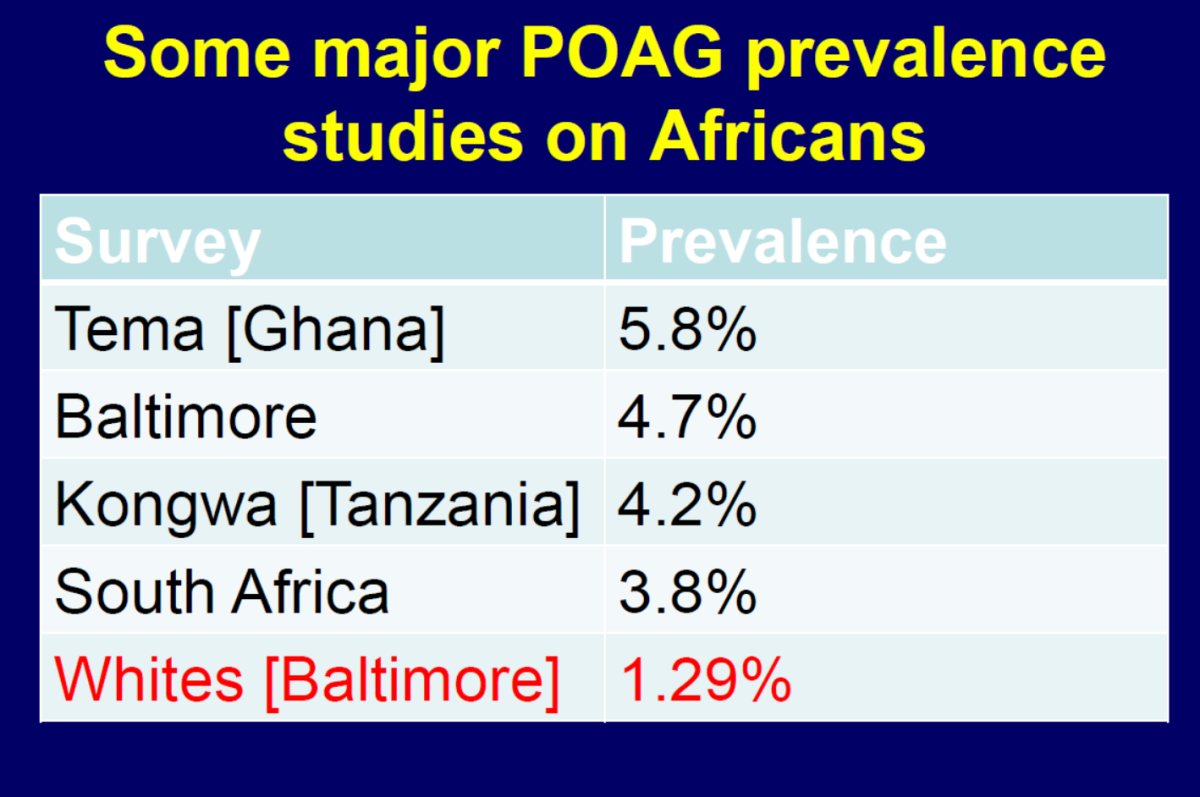
POAG 5% in > 40 year old black Africans
Glaucoma in South Africa and Africa
- In SA, 5% of the Black population > 40 years has glaucoma, starts earlier and is more aggressive
- Similar numbers are reported for Black Cameroonians
- In the white populations its about 1.5%
Rotchford & Johnson. Arch Ophthalmol. 2002 Apr; 120(4):471-8.
Rotchford et al. Ophthalmology. 2003 Feb; 110(2):376-82.
Salmon et al. Arch Ophthalmol. 1993 Sep; 111(9):1263-9.
Ellong et al . Sante. 2006 Apr-Jun;16(2):83-8.
- The SA prevalence is lower than estimates of 7% for Blacks in Ghana and in Barbados (Caribbean)
Ntim-Amponsah et al. Eye (2004) 18, 491–497.
Fatima Kyari et al. Middle East Afr J Ophthalmol. 2013 Apr-Jun; 20(2): 111–125
Predicting the Glaucoma Burden of Care in South Africa
- According to South African Government statistics (2014), 43,333,700 Blacks reside in South Africa
- 10.5 million of them are older than 40 years
- If 5% of them have glaucoma then the number of Black citizens in South Africa with glaucoma is 525,000
What is the projected burden of glaucoma care in South Africa and Nigeria
South African Glaucoma Society Guidelines and European Glaucoma Society Guidelines state the following:
Every new glaucoma patient should receive:-
- Comprehensive clinical examination including slit-lamp examination, tonometry, fundus and optic nerve head examination, gonioscopy, and corneal thickness measurement.
- Special investigations to document the extent of structural damage to the optic nerve head and the retinal nerve fiber layer: OCT, disc photography, computer assisted visual field analysis
- Comprehensive discussion and information session to answer questions and educate the patient on the disease
Glaucoma
Management
- Follow-up:
- FOR CONTROLLED PATIENTS: Patients should be seen 3 times per year
- At each visit the following should be performed:
- Review of possible side effects, drug efficacy, compliance, new medical history
- Comprehensive clinical examination including slit-lamp examination, tonometry, optic nerve head examination and gonioscopy
- Disc and nerve fiber analysis (1 per year)
- Disc photography (1 per year)
- Computer assisted visual field analysis (2 per year )
- Retinal threshold trend evaluation (1 per year)
- Follow-up:
- FOR UNCONTROLLED PATIENTS: Patients may need to be seen up to 6 times per year
- At each visit the following should be performed:
- Review of possible side effects, drug efficacy, compliance, new medical history
- Comprehensive clinical examination including slit-lamp examination, tonometry, optic nerve head examination and gonioscopy
- Special examinations must be repeated:
- Disc and nerve fiber layer analysis (2 per year)
- Disc photography (2 per year)
- Computer assisted visual field analysis (3 per year)
- Retinal threshold trend evaluation (3 per year)
Let’s Do the Math
- 525,000 cases of glaucoma in just the Black community in South Africa
- If we assume that half are stable and half are not, then the EGS guidelines require 3 visits per year for controlled patients (787,500 in SA)
- In uncontrolled cases up to 6 (assume 5) visits per year adds another 1,3 million visits in SA
- TOTAL = 2.1million visits are needed to take care of non-surgical glaucoma in SA
- Assuming each visits lasts only 15 minutes, that would require 525,000 hours in SA
- Note that this is only “doctor time” and assumes there are assistants doing all ancillary tests (and leaving no time for the doctor to later review any of these tests)
- A person working a 40 hour work week for 48 weeks/year equals 1,920 hours per year
- To provide 525,000 hours of care would require 273 ophthalmologists working full time, SOLELY on the non-surgical, medical care of glaucoma patients –not counting any care for cataract, diabetic retinopathy, macular degeneration or even glaucoma surgical care (not to mention routine red eye cases, all other eye diseases)
…and thats before we even begin to talk about the Diabetes tsunami
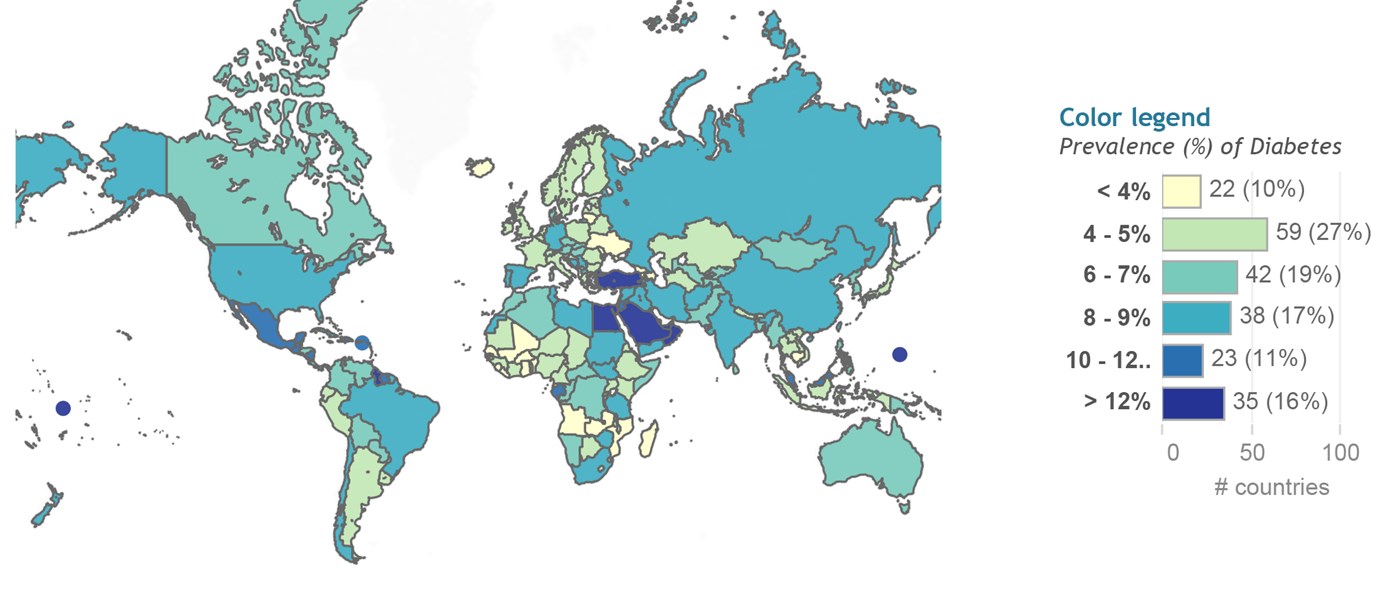
- In 2015, 415 million people world wide had diabetes, this included 14 million people in Africa
- It is projected that these figures will double by 2040
Diabetic retinopathy

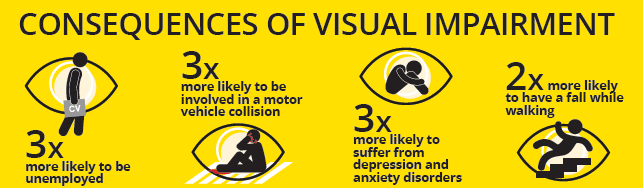
Impacts of Vision Loss
- Less access to health support services
- Loss of independence and dignity
- Need for greater social support
- Women and girls suffer most
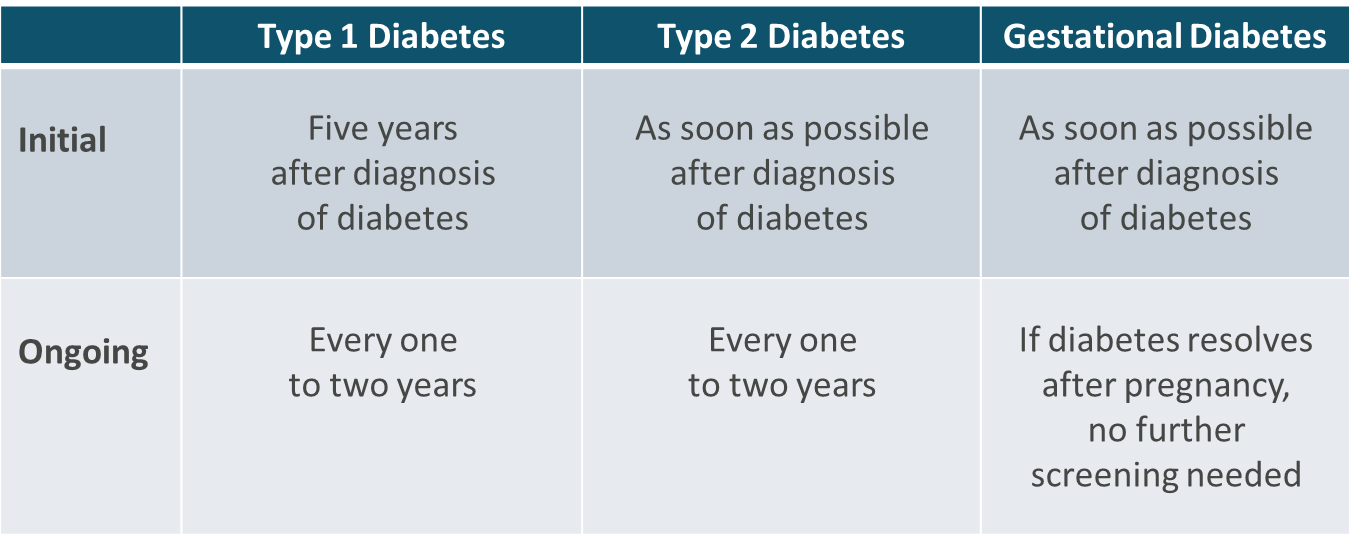
Timing of Eye Screening
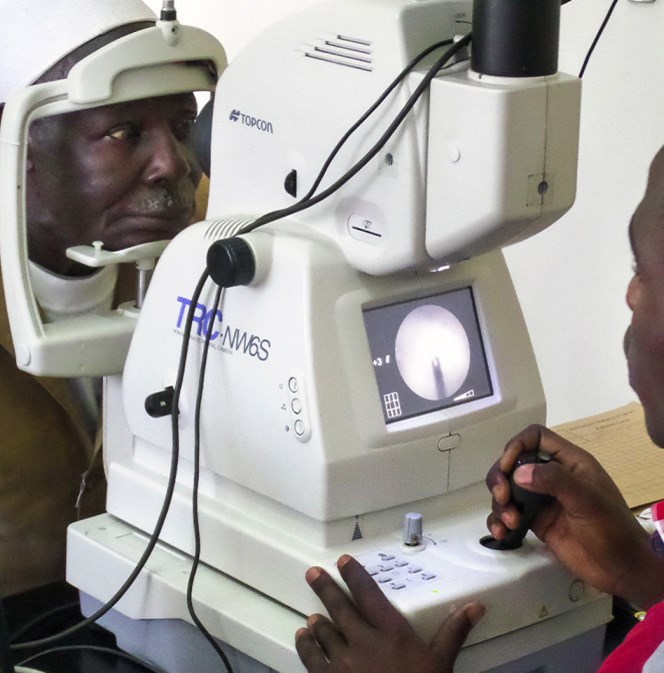
Retinal Examination

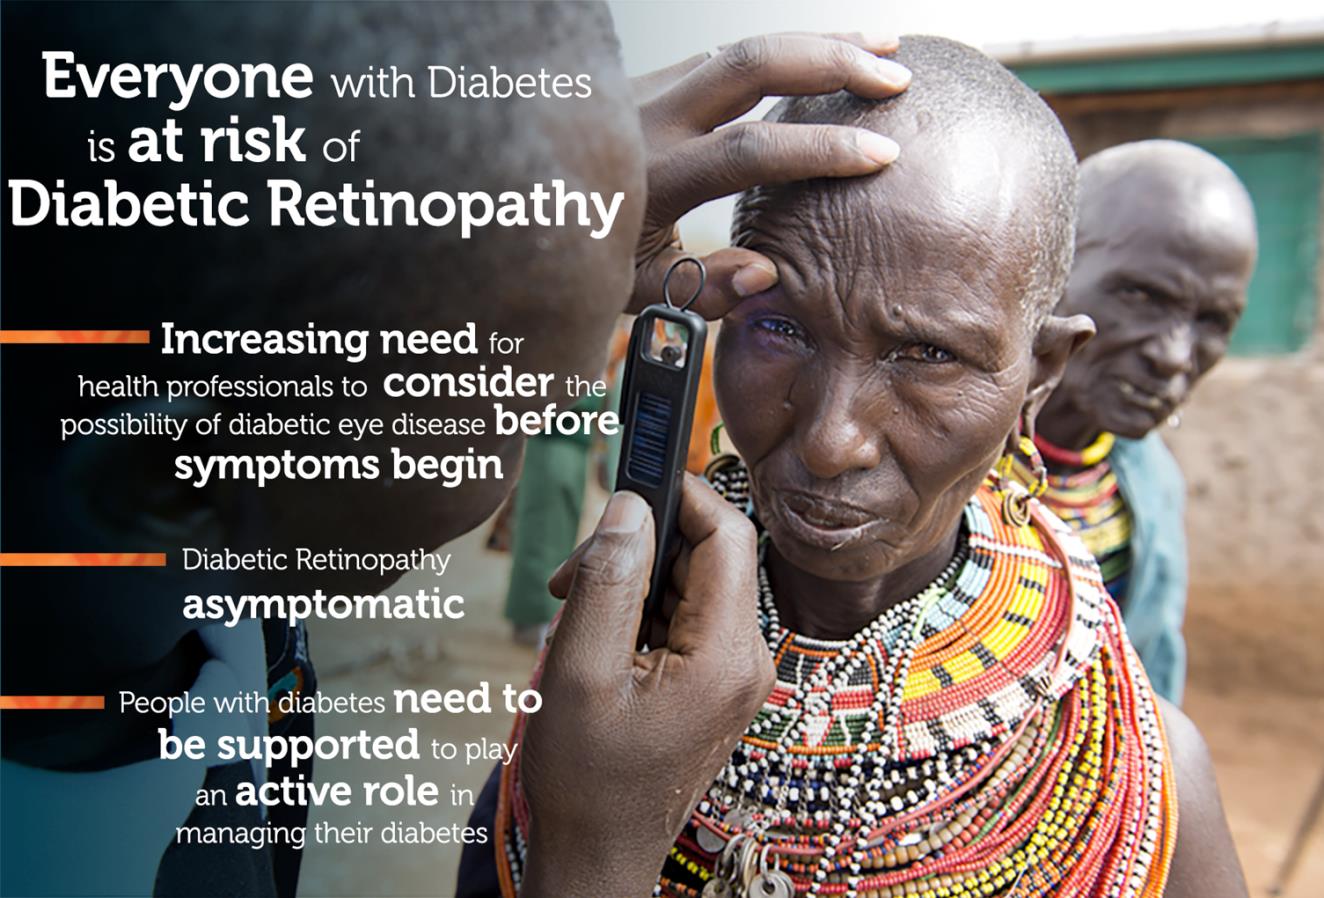
Diabetes in South Africa
- Prevalence of diabetes is 11-13% among the Indian population, 8-10% in the mixed race community, 5- 8% among blacks and 4% among whites
- 2,3 million aged 20 -79 have diabetes
- 1,4 million aged 20 -79 are undiagnosed
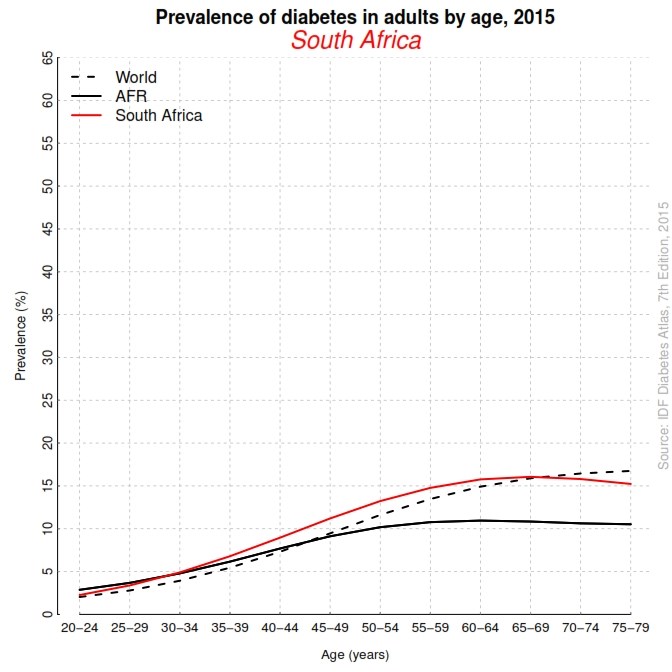
Let’s do the math
- The numbers here are much harder to calculate but if we assume just 1 dilated exam annually averaging 10 min, not counting time to dilate
- 383,000 hours of care per year in SA
- Again, one person working a 40 hour work week for 48 weeks/year equals 1,920 hours per year.
- That’s another 200 ophthalmologists doing nothing but dilated fundus examinations on KNOWN diabetics once a year, without any FAs, no PRPs, no vitrectomies…..
How should the gap be filled?
There are three options:
- Dramatically increase the output of ophthalmologists
- Create a new medical specialty of non-surgical ophthalmology that could be trained quicker and cheaper than surgeons
- Fundamentally upgrade the training of optometrists, freeing surgeons to do more surgery and vastly increasing the portals of entry for routine medical eye care
- Add more assistants, nurses, to the staff of the present number of ophthalmologists, teaching them to manage disease under the direct supervision of an ophthalmologist
Upgrade the training of optometrists
- ADVANTAGES
- Much broader access to care in widely dispersed community-based clinics overseen by independently registered optometrists
- Individuals providing care are each personally liable for their care
- DISADVANTAGES
- This will require invention and training of a provider very different from today’s average optometrist
- Optometry training world wide is not standardized – implementation of National and African board examinations
This option is the one that has been chosen most often around the world
Decolonisation of education
- The first optometrists in Africa were trained in Britain
- Optometric education in Africa followed the British system until recently when Nigeria and Ghana introduced the American doctor of optometry program
- Many institutions adopted outcomes based education systems which led to “dumbing down” of university education programs including optometry
- World wide and specifically in Africa optometric education is in need of standardisation, ensuring the standards and quality of graduates are of the highest level
- Africa needs clinicians as well as researchers, one cannot exist without the other
- More postgraduate and residency programmes for optometrists in Africa must be established – funding for these programs?
Recognition and Legalization
- The establishment, recognition and development of any profession depends on the perceived need for the profession in that country
- Great efforts have been made towards developing the profession of optometry, yet we fail to reap the rewards!
- Although recognized legally, optometry still face a tremendous challenge of being given full recognition by major actors in the health care system throughout Africa
- Development of optometry in Africa has been adversely affected by opposition from organised medicine, lack of scope and slow legislative changes, inadequate education, poor service delivery and lack of posts in public health institutions

“Optometry is supposed to be part of the primary healthcare system but it hasn’t yet been integrated into the system….”
Dr Udak Christabel Udom – President of the WCO and past president of AFCO and NOA
What should the scope of and optometrist be?
- Optometrists should function as primary and secondary eye care providers who are especially experienced in:
- Conducting routine comprehensive eye exams
- Fitting contact lenses and determining eyeglass prescriptions
- Treating and managing common eye diseases such as red eye, glaucoma, anterior uveitis, diabetic retinopathy and dry eye syndrome
- When patients require tertiary care and surgical management, optometrists will often refer and co-manage with ophthalmology
- When systemic conditions are suspect, today’s optometrists will co-manage medical cases with other medical specialties including internal medicine, emergency medicine, neurology, rheumatology, dermatology, paediatrics, oncology, and radiology
Conclusion
- Optometrists must become primary eye care providers, working closely with organised medicine to provide care and eliminate the great need for eye care that exist on the African continent
- This requires an overhaul of the current educational system including standardization of education, and changes in legislation as well as scope of practice
- Implementation of a African Optometry board examination – AFCO?
- We need to seek education solutions unique to Africa, whilst ensuring that the our clinicians are rated among the best in the world
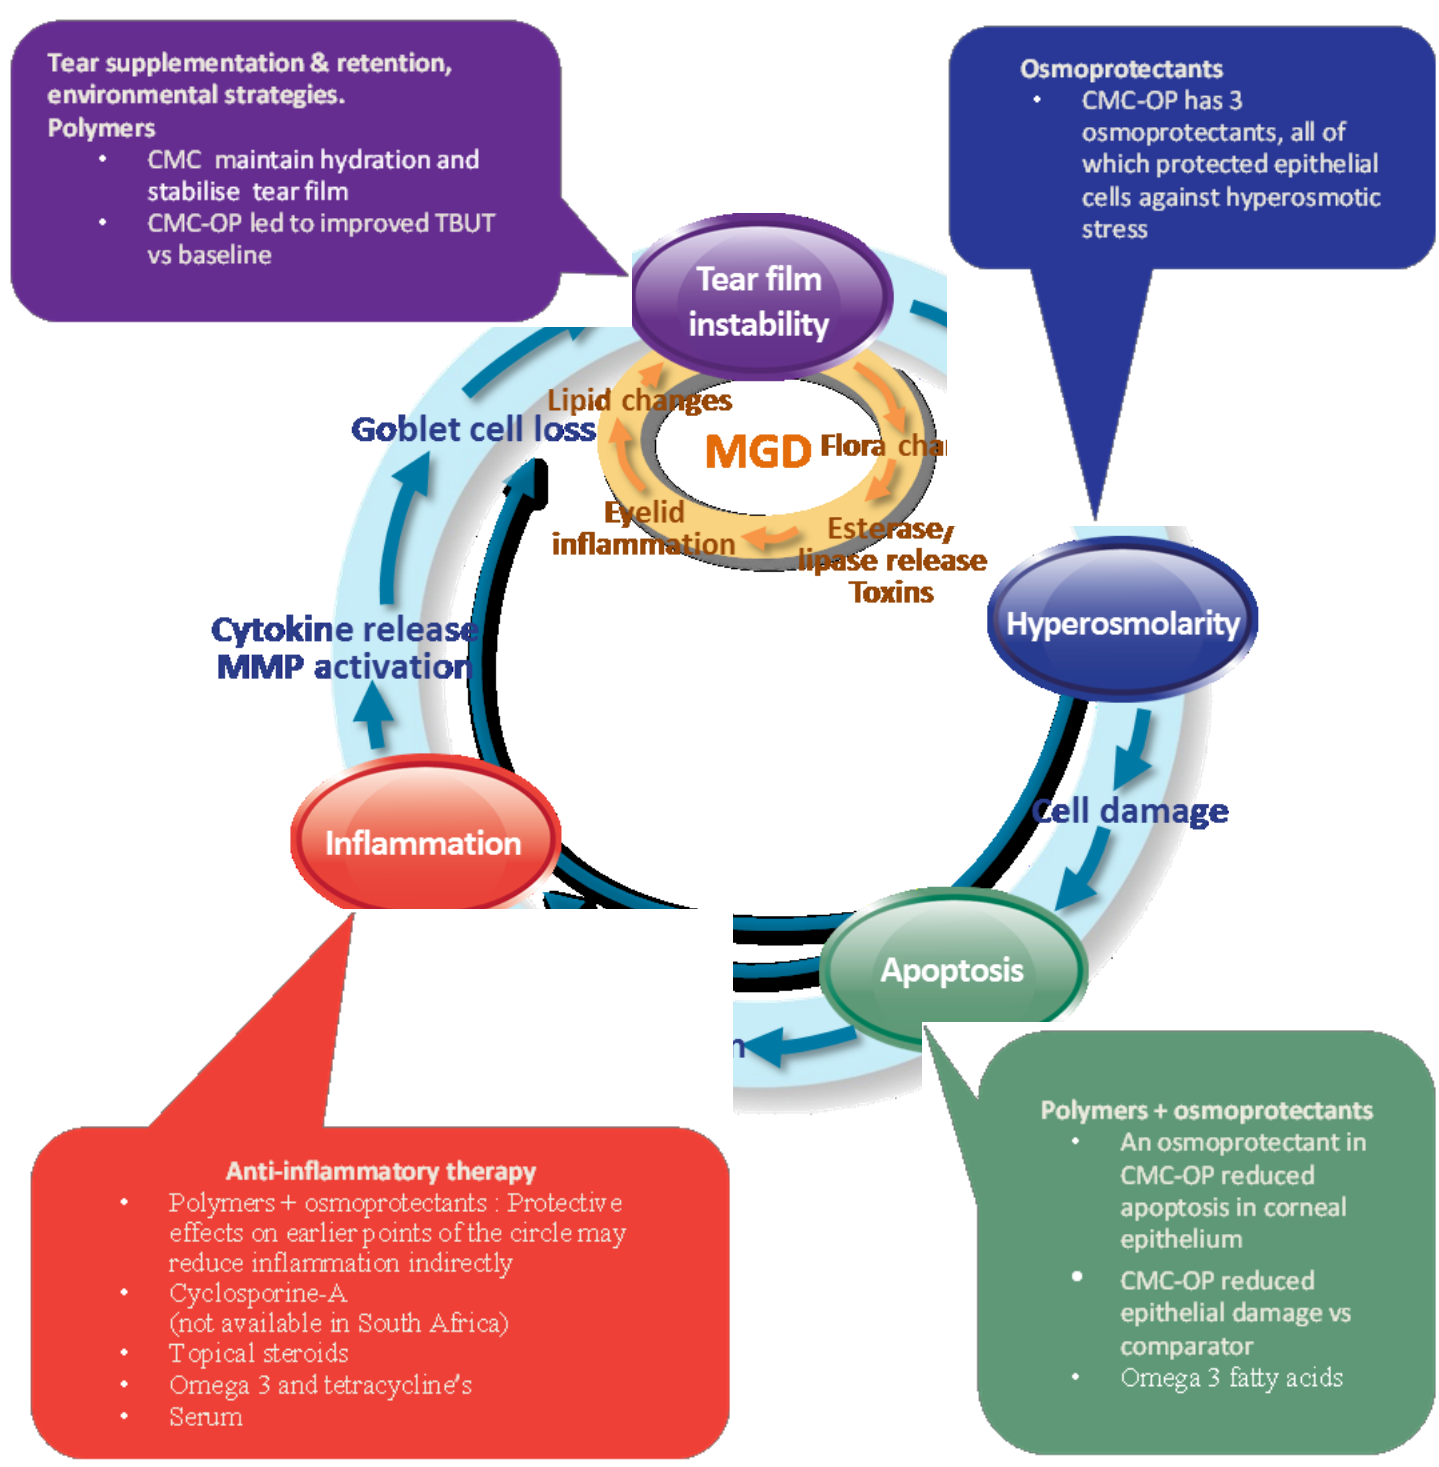
The influence of each mmHg IOP reduction on functional progression
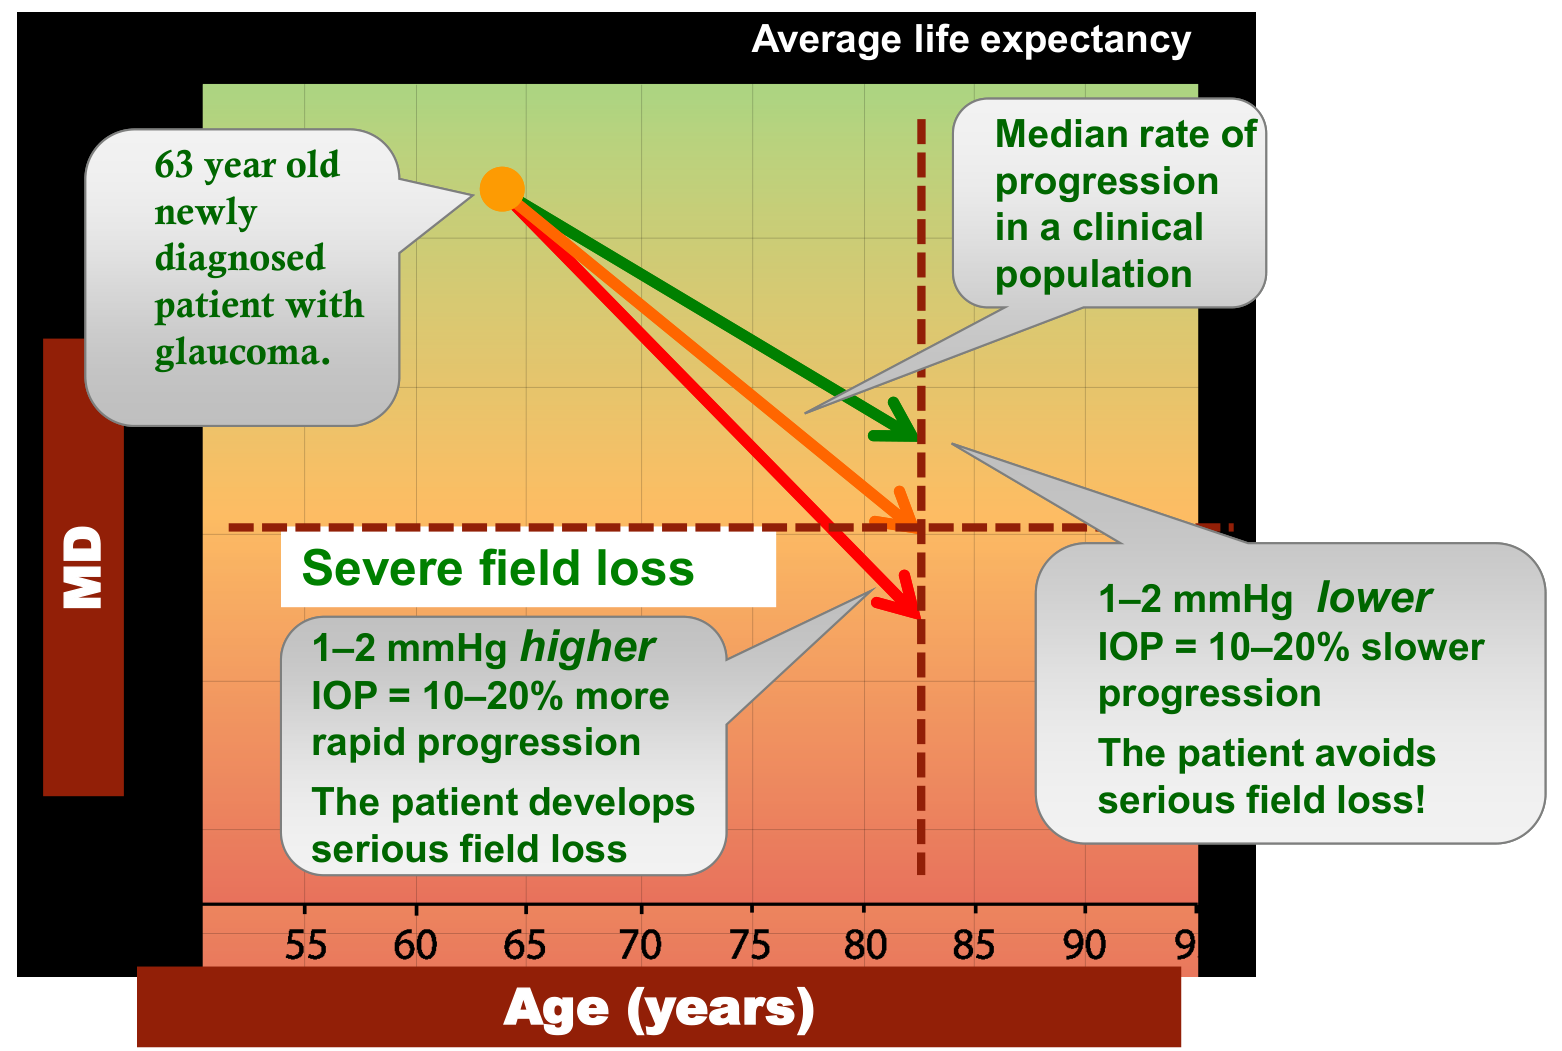
By changing the visual field rate of progression, a patient’s QoL can be preserved for longer
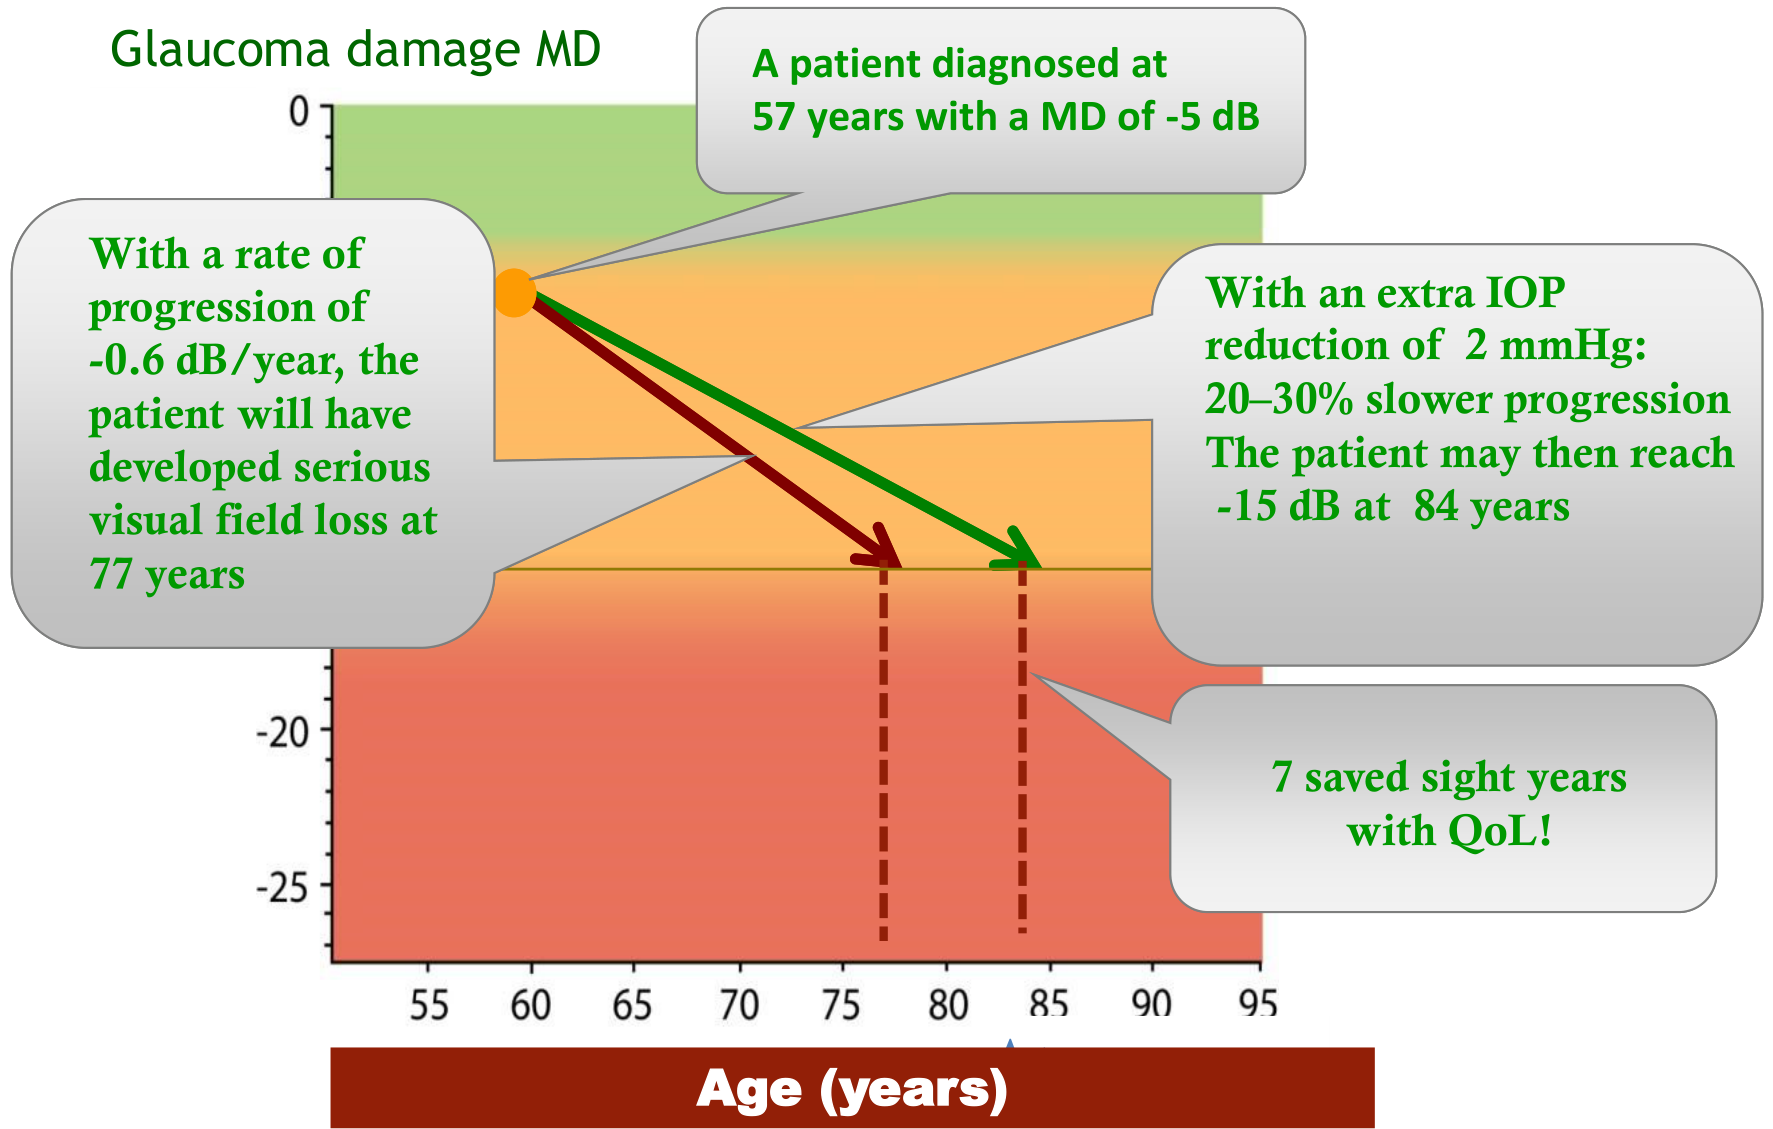
The “vicious” dry eye cycle showing the four key areas as well as most appropriate therapeutic interventions. Figure adapted from Baudouin et al. (2013)
CMC – carboxymethylcellulose, CMC-OP – carboxymethylcellulose + erythritol, glycerol, L-carnitine.
Case 1
- 55 year old Caucasian male.
- Complains of red eye lasting more than 1 week.
- Went to GP who prescribed tobramycin qid and Spersallerg tds.
- No improvement.
- VA right and left 20/25.
- IOP right and left 13mmHg.
- Anterior chamber clear, pupil reaction normal as well as the posterior pole.
- Your diagnosis and treatment strategy.
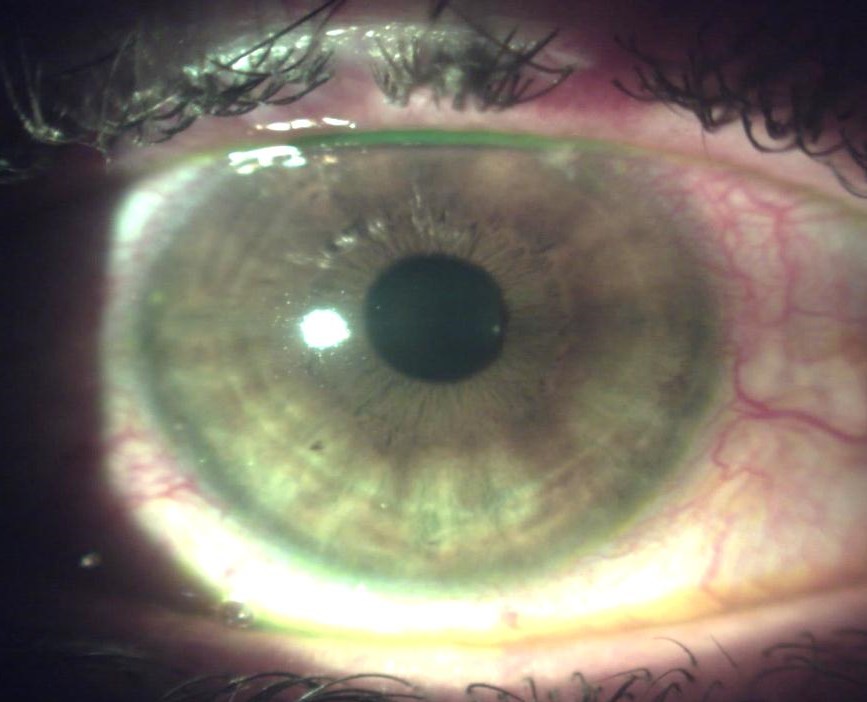
Anterior segment photos
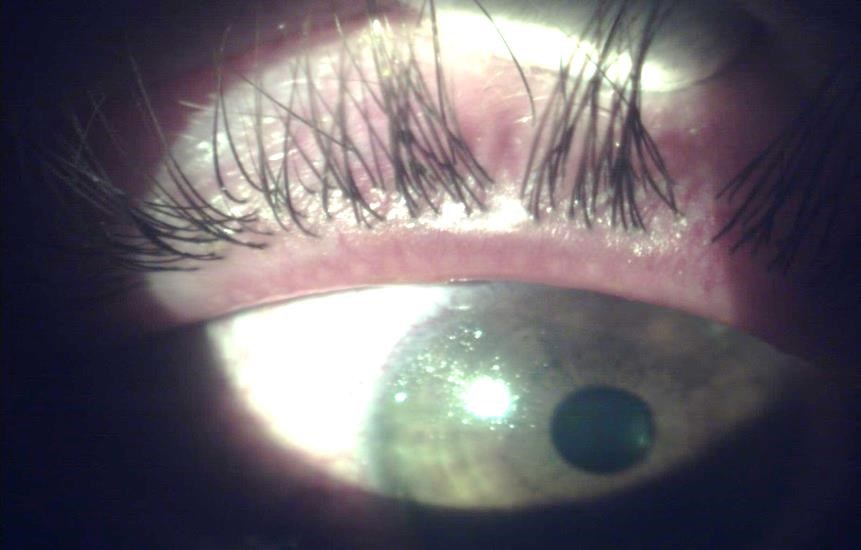
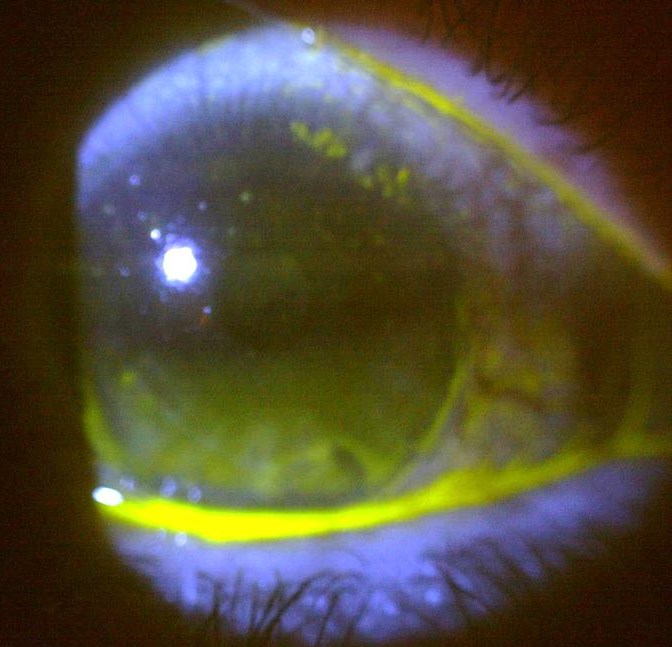
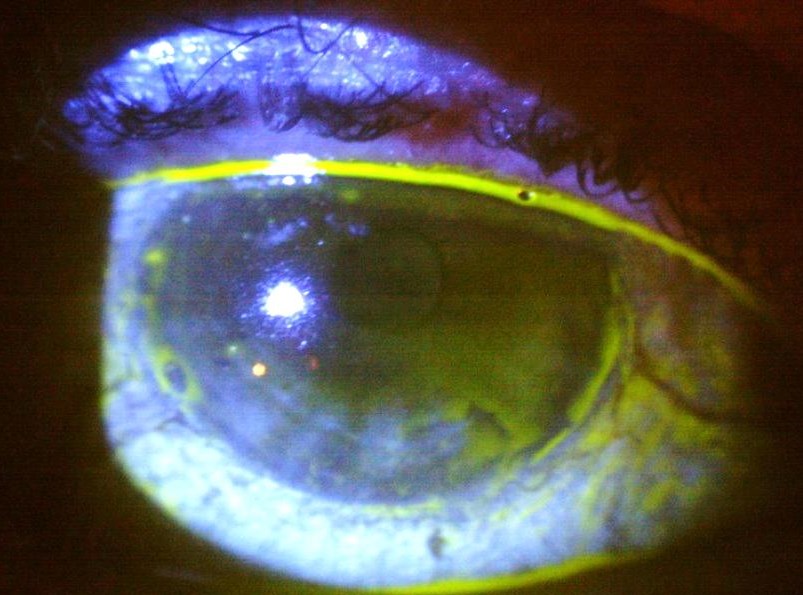
Diagnosis and treatment
- Non contact lens wearer with marginal infiltrative keratitis, posterior blepharitis not responding to treatment with tobramycin.
- Diagnosis – Staph hypersensitivity
- Treatment included steroid/antibiotic combination. Spersadex Comp. qid as well as Exocin qid.
- Both cover gram positives well (tobramycin more gram negative specific).
- Futher treatment was lid hygiene, IBag, and Systane lid wipes which is a new product from Alcon.
- The condition completely resolved within days
Case 2
- 78 year old female patient with complaints of severe discomfort in both eyes.
- Recently saw a colleague who prescribed artificial tears. Very photophobic, difficult to open eyes during examination.
- On HRT but general health is good.
- Previously her acuity was 20/30 in both eyes
- The posterior pole was normal and IOP was right 12 and left 10mmHg.
- She had pterigiums removed in both eyes.
- At this stage she has central lens opacities in keeping with the age group.
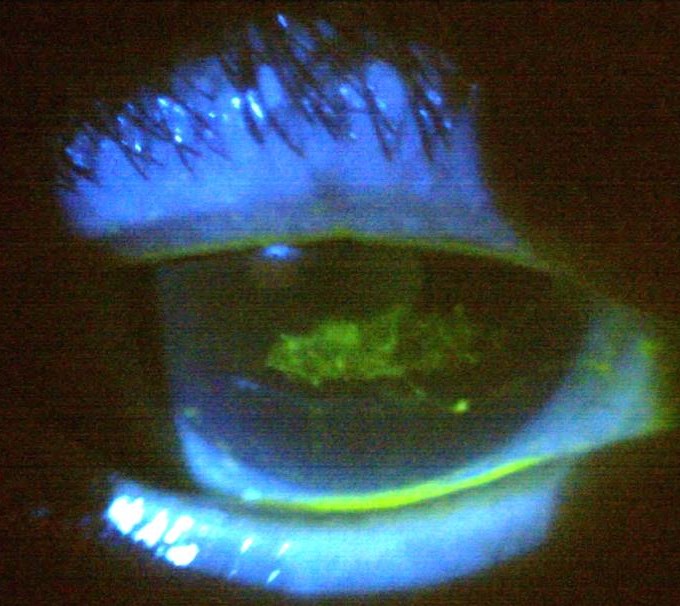
Anterior segment photos
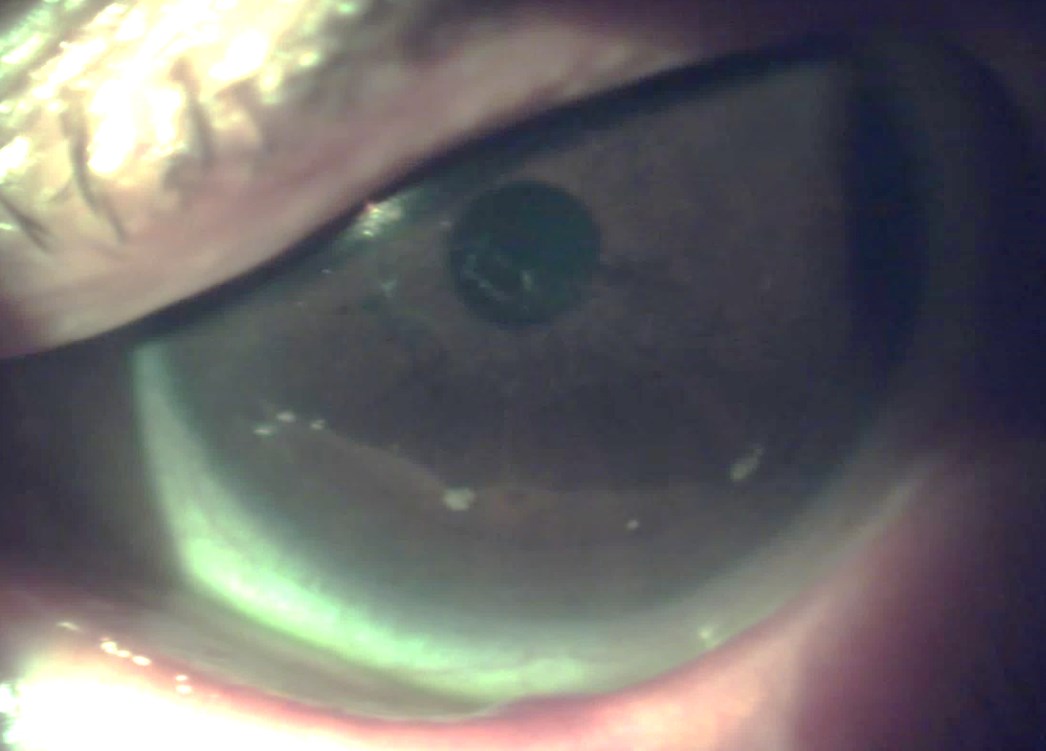
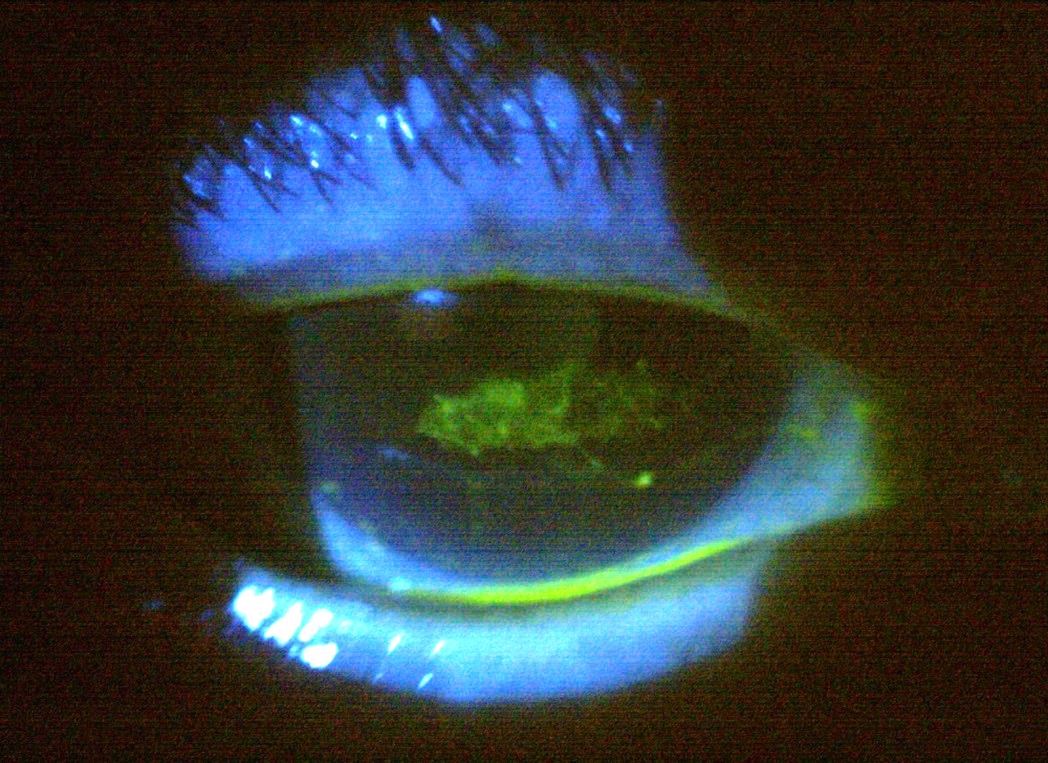
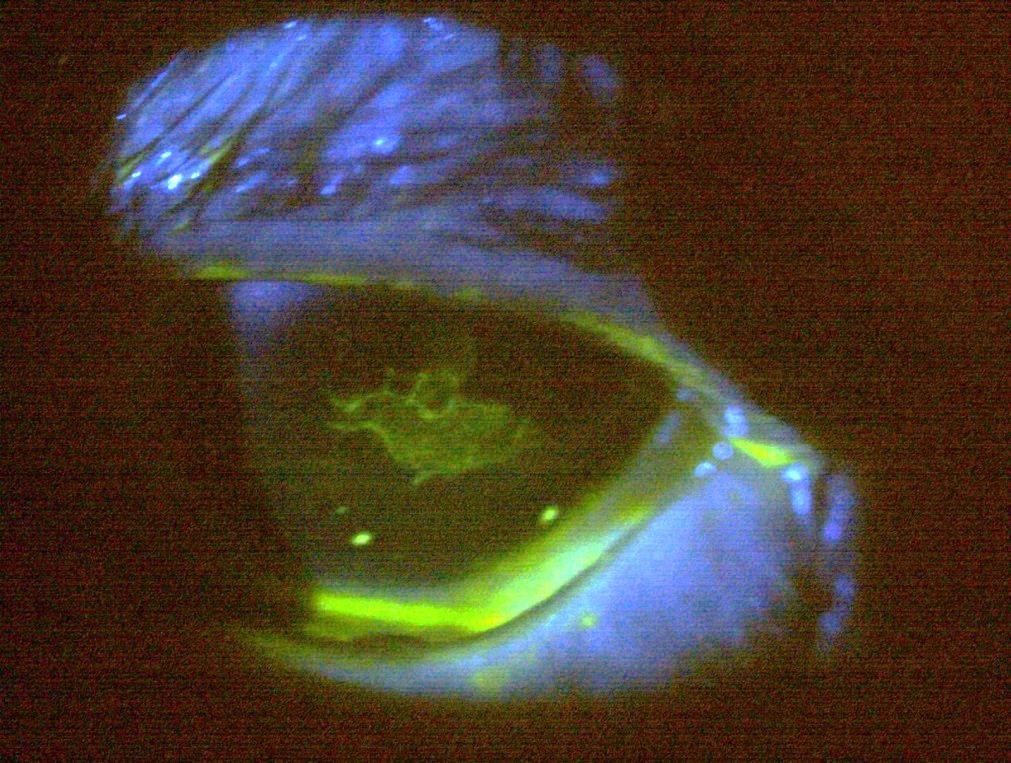
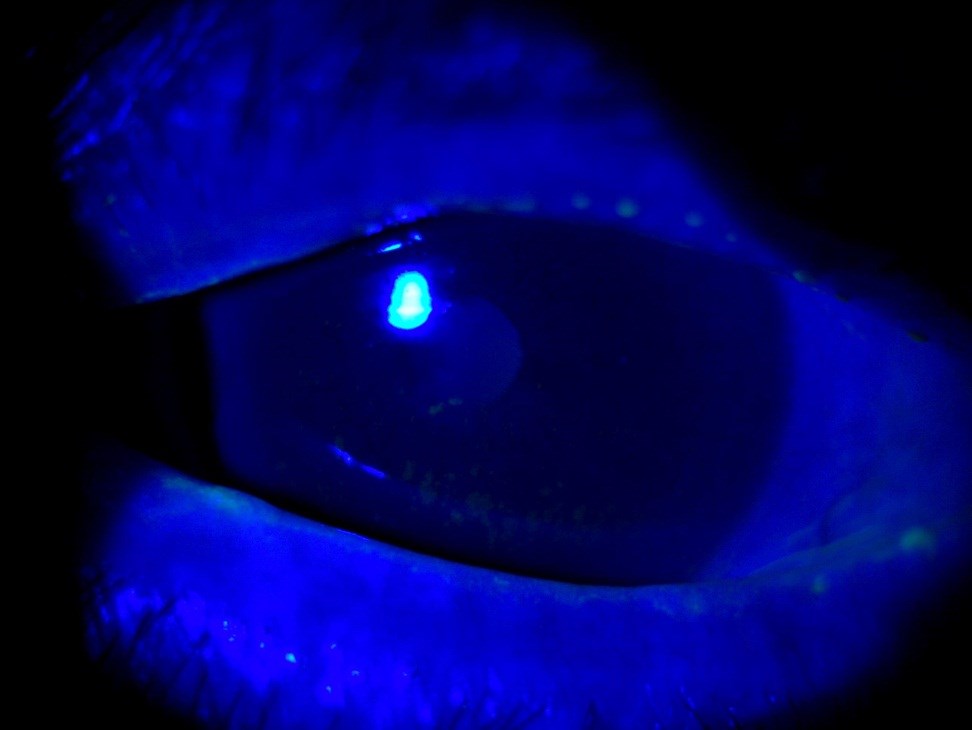
- Note the lesion which lies centrally on both eyes in the pupil, difficult to photograph due to discomfort so excuse the slightly blurry images.
- The lesions stain in both eyes with lots of mucus strands evident
Diagnosis and treatment
- Keratoconjunctivitis sicca
- Large central epithelial defect, mucus strands
- Treatment:
- Bandage contact lenses worn on extended wear basis (-0.50 Acuvue Oasys®)
- Exocin qid plus FML qid
- Preservative free lubricants prn
Case 3
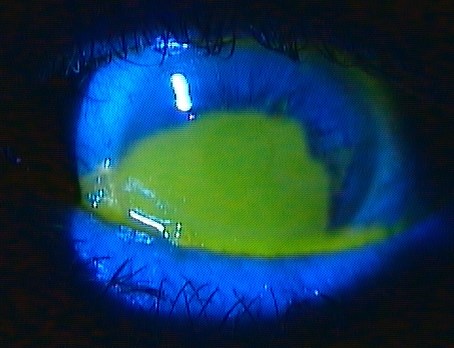
- This lady presented with a history of trying to clean a dark spot on her ceiling.
- She visited the local hospital emergency unit where she received a tube of Maxitrol ung.
- She arrived at our rooms on the Monday morning in lots of pain and desperate for help.
- Her eye was severely red
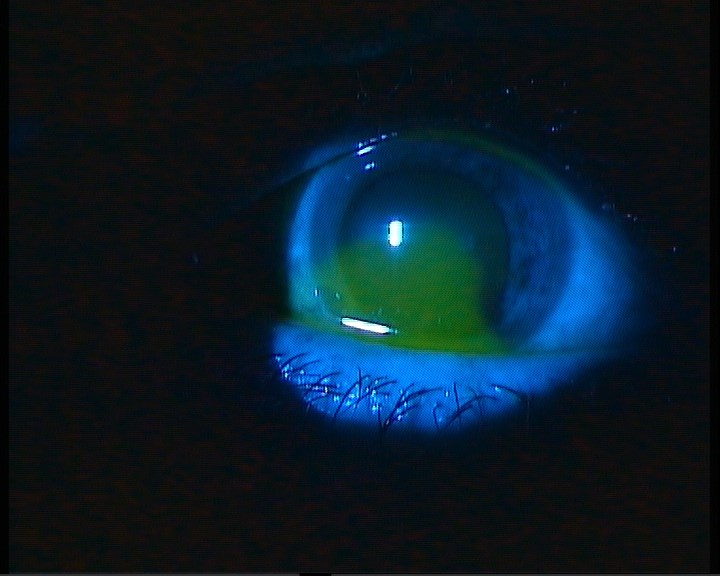
- She had lost more than 60% of the corneal epithelium as well as a large chunk of the conjunctival epithelium in the 7h00 to 8h00 bulbar area
- VA 6/60- and she was not quite lucid after taking a vast amount of pain killers.
- How would you proceed with treatment?
Treatment
- Establish the cause, trauma, acid or alkaline burn?
- Copious Irrigation – 15 to 30 minutes
- Cyclomydril stat
- Bandage lens, Acuvue Oaysys® -0.50D
- Exocin q2h
- Follow up daily or at least every second day
Ehlers, J.P, Shah, C. P. The Wills eye manual, 5th edition

Day Two after treatment
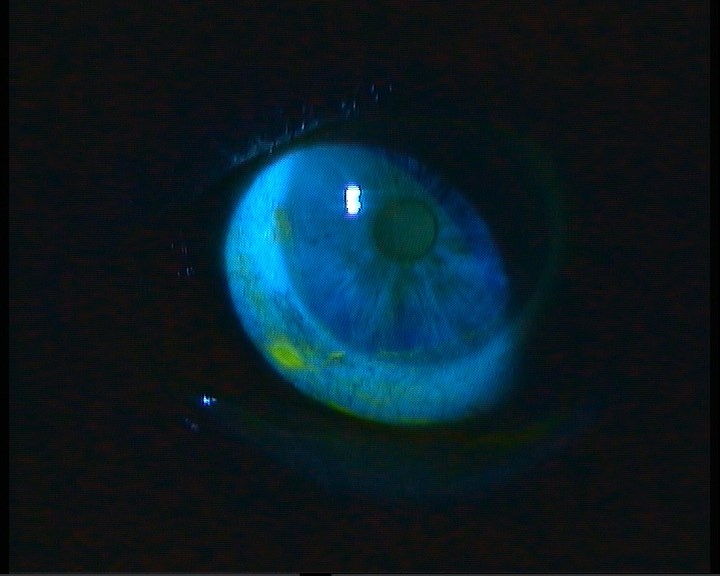
Day 6 after treatment
Resolution
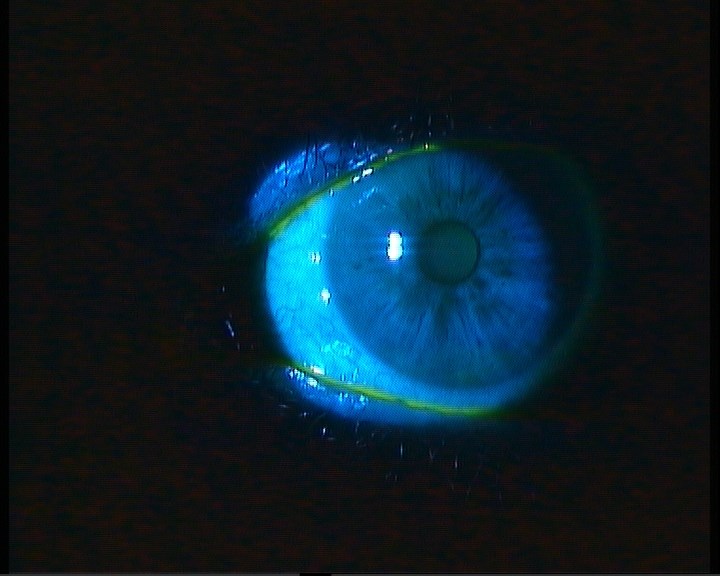
Case 5
- 60 year old lady, right unilateral ptosis, discomfort, lots of mucus discharge, red eye.
- No influence on her vision but very uncomfortable. This problem waxes and wanes.
- Your diagnosis and best treatment strategy?
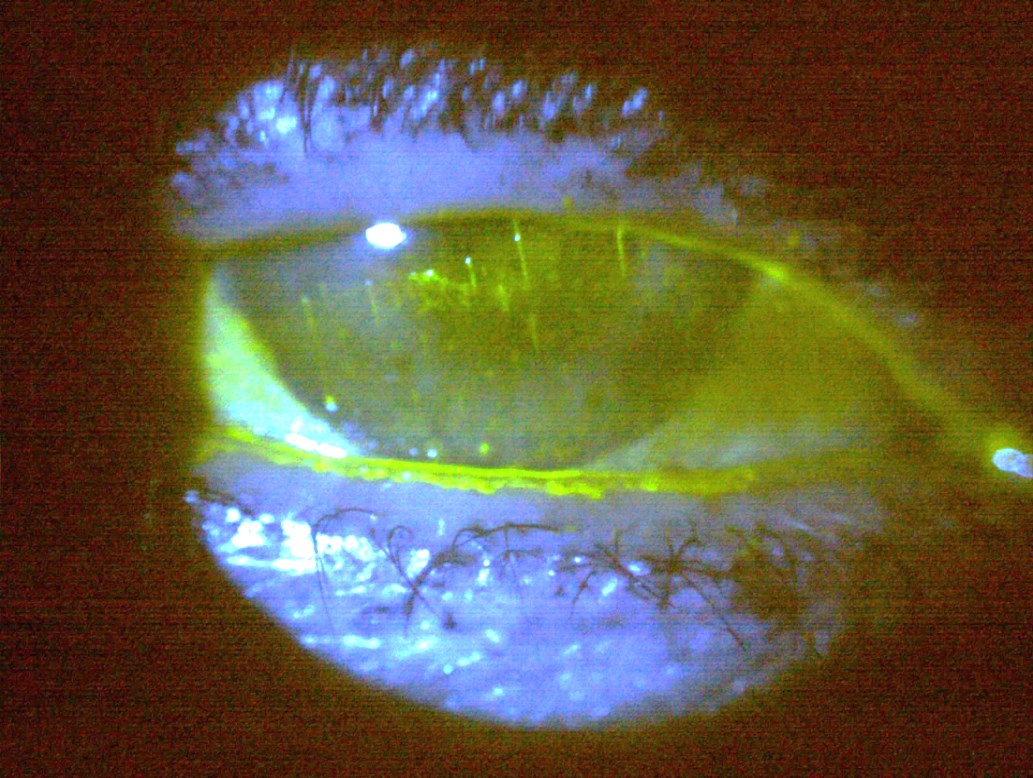
Diagnosis
- Severe keratoconjunctivitis sicca with filamentary keratitis, ptosis, and mucus fishing, she digs these strands of mucus out of the eye making the situation worse.
- Treatment consisted of:
- Punctal plugs both inferior and superior,
- Bandage contact lens,
- FML q2h to taper to bid,
- Lots of lubrication – optive and systane q2h
- This combination works well as glycerine hydrates and HP guar holds the tear film in place.
Treatment and follow-up
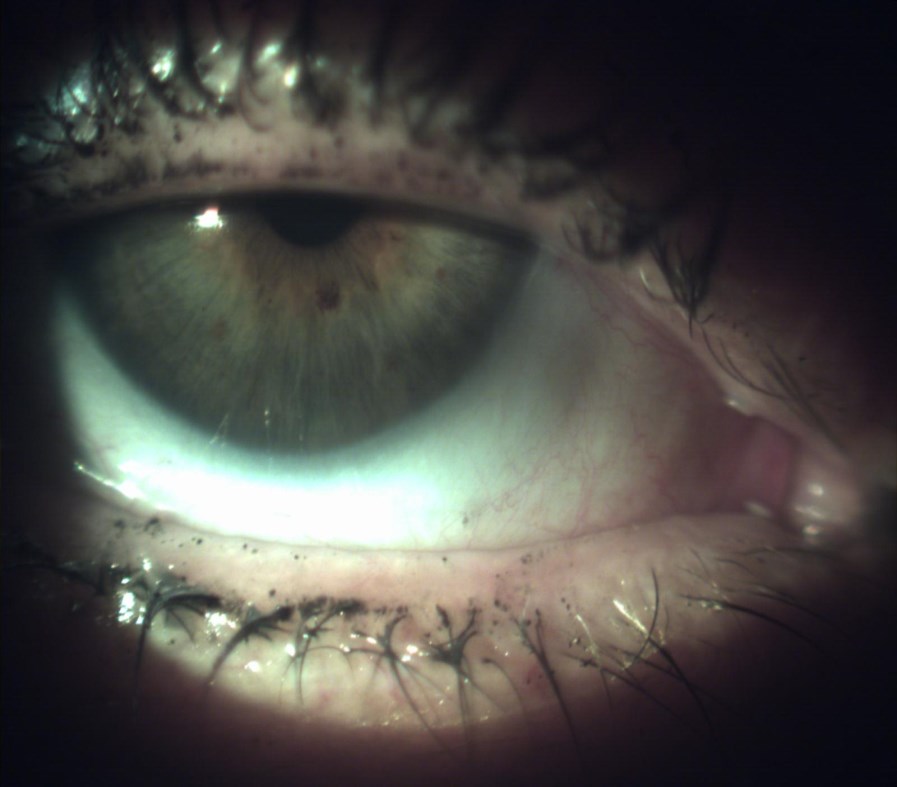
- Now been two weeks with the bandage lens and she feels great, ptosis has also improved.
- Note plugs in inferior as well as superior puncta
- Reduce FML to once per day and kept her on the lubricants.
- Plan is to keep bandage on for a week then get rid of it and watch her carefully
- She may need pulse therapy with the FML to maintain the status quo
- Be sure to regularly monitor the IOP
Thank you
